
 Home
Minimally Invasive Endocrine Surgery
Minimally invasive thyroid, parathyroid and adrenal surgery in Monmouth County, NJ
Dr. Alexander Shifrin is Director of Endocrine Surgery at CentraState Medical Center in Freehold and performs more than 400 thyroid and parathyroid operations a year. Small incisions, nerve monitoring, no drains, and same-day discharge for most thyroid and parathyroid patients.
Call (732) 792-5003 or request a consultation. Office: 55 Willow Ln, Suite 101, Englishtown, NJ.
Jump to: At a glance Thyroid surgery Parathyroid surgery Adrenal surgery What to expect Choosing a surgeon References
Reviewed by Alexander Shifrin, MD, Director of Endocrine Surgery, CentraState Medical Center.
Minimally invasive endocrine surgery at a glance
| Thyroid | Parathyroid | Adrenal | |
|---|---|---|---|
| Operation | Removal of half (lobectomy) or the whole thyroid | Removal of one or more enlarged parathyroid glands (adenomas) | Removal of the tumor or the whole gland |
| Incision | One small mid-neck incision in a natural skin crease | One small transverse neck incision in a skin crease | Three small incisions (laparoscopic), from the abdomen or the back |
| Anesthesia | General anesthesia with nerve monitoring (very rarely regional block) | Most often a neck block with sedation, like a colonoscopy | General anesthesia |
| Drains | None | None | Not routinely |
| Closure | Dissolvable stitches under the skin, or skin glue | Dissolvable stitches under the skin, or skin glue | Small incisions closed with sutures or glue |
| Hospital stay | Usually same day, about 6 hours of observation | Usually same day, about 3 hours of observation | Most often overnight |
| Read more | Thyroid surgery | Primary hyperparathyroidism | adrenaltumors.org |
A) Minimally invasive thyroid surgery
Minimally invasive thyroid surgery is the removal of one half or the whole thyroid gland through a small mid-neck incision placed in the natural skin crease. It is performed under general anesthesia or, very rarely, under a local-regional block. Under general anesthesia, the recurrent laryngeal nerve (which controls the voice) and the external branch of the superior laryngeal nerve are monitored during the operation. Minimally invasive surgery also includes video-assisted or endoscopic thyroidectomy, in which the surgeon uses a camera to magnify the view. This speeds healing and reduces scar formation.
- No drains or tubes are left in after surgery.
- The skin is closed with dissolvable stitches under the skin or with skin glue, and no stitches need to be removed.
- Surgery is usually same-day. The patient stays in the hospital for about 6 hours of observation. The American Thyroid Association states that outpatient thyroidectomy can be done safely in carefully selected patients.
Who needs thyroid surgery?
- Thyroid cancer or a suspicious nodule. The 2025 ATA guideline allows a lobectomy for many low-risk cancers up to 4 cm and recommends total thyroidectomy when the cancer is larger or higher risk. See thyroid cancer, thyroid nodules and thyroid biopsy.
- Graves' disease or toxic nodular goiter. See Graves' disease and toxic nodular goiter.
- A large goiter causing pressure, trouble swallowing or breathing.
- Hereditary thyroid cancer syndromes, such as MEN 2.
B) Minimally invasive parathyroid surgery
Minimally invasive parathyroid surgery is the removal of one or several parathyroid glands (adenomas) through a small transverse mid-neck incision, placed in the natural skin crease. It includes open parathyroidectomy through a small incision and video-assisted or endoscopic parathyroidectomy, in which the surgeon uses a camera to magnify the view. This speeds healing and reduces scar formation.
- Localization first. To make a minimally invasive approach possible, the adenoma must be located before surgery with a neck ultrasound and a sestamibi (parathyroid) scan. Other imaging, such as 4D CT, can be added when these tests do not agree.
- Intra-operative PTH monitoring. Dr. Shifrin uses intra-operative parathyroid hormone (PTH) monitoring to confirm the cure during the operation, right after the adenoma is removed.
- Anesthesia. Most patients have a neck block (regional anesthesia) with general sedation, as is done for colonoscopy.
- One gland in most patients. About 85% of patients with primary hyperparathyroidism have a single parathyroid adenoma.
- No drains. The skin is closed with dissolvable stitches under the skin or with skin glue. It is usually same-day surgery, with about 3 hours of observation.

Intra-operative PTH monitoring
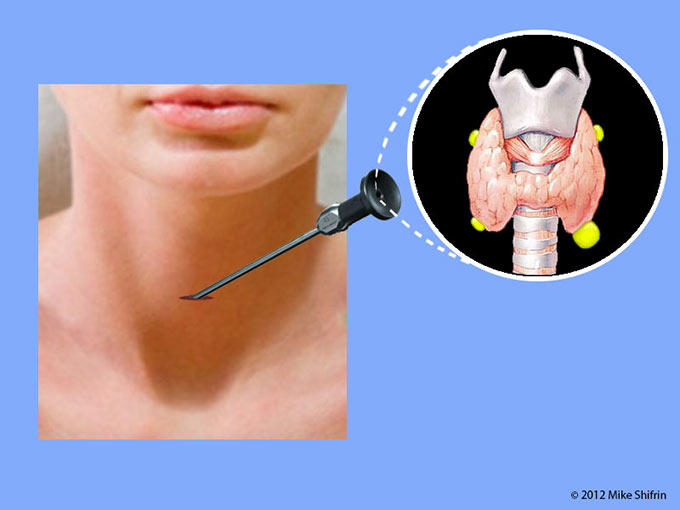
Click on the image to view the video "Minimally Invasive Video-Assisted Parathyroidectomy"
Who needs parathyroid surgery?
Surgery is the only cure for primary hyperparathyroidism. The 2022 Fifth International Workshop guideline recommends surgery to cure the disease, even in patients without symptoms (strong recommendation), and especially for patients with kidney stones, reduced kidney function, osteoporosis or fractures, calcium well above normal, or age under 50. See primary hyperparathyroidism and the hyperparathyroidism FAQ.
C) Minimally invasive adrenal surgery
Minimally invasive adrenal surgery is the laparoscopic removal of the adrenal tumor only (partial adrenalectomy) or of the entire gland with the tumor. It can be done through the abdomen or through the back:
- Laparoscopic transabdominal lateral adrenalectomy: through the abdomen.
- Posterior retroperitoneoscopic adrenalectomy (PRA): laparoscopic surgery through the back, directly to the gland.
Dr. Shifrin considers the posterior approach the most advanced option for suitable patients. Patients have minimal pain, can return to normal activities very quickly, and have the best cosmetic result, with three small incisions instead of one large incision used in open surgery. Only a limited number of endocrine surgeons in the country perform PRA, because it requires a high level of expertise and advanced training. Most patients stay overnight and go home the next day. See the video below, and for more information and pictures, visit adrenaltumors.org.

Who needs adrenal surgery?
- Hormone-producing tumors: aldosterone-producing adenoma (primary aldosteronism), cortisol-producing tumors (Cushing syndrome or mild autonomous cortisol secretion), and pheochromocytoma.
- Tumors that look suspicious on imaging, or that are growing.
- Surgery is not usually needed for a small, non-functioning mass with clearly benign features on imaging.
The 2022 American Association of Endocrine Surgeons guideline recommends minimally invasive adrenalectomy over open surgery when the patient and tumor are suitable, by either the retroperitoneal (back) or transperitoneal (abdominal) route, depending on surgeon expertise. The 2023 European guideline recommends laparoscopic surgery for benign tumors up to about 6 cm. Suspected adrenal cancer is usually treated with open surgery. Both guidelines advise that adrenal surgery be done by a high-volume surgeon.
What to expect: your surgery journey
Review of tests, scans and your options
Imaging, blood tests, medicines adjusted if needed
Small incision, nerve monitoring, no drains
Same day for most thyroid and parathyroid patients
Calcium, thyroid or hormone tests, and the pathology report
Risks
All operations carry risk. For thyroid surgery the main ones are injury to the voice nerve (hoarseness), low calcium from the parathyroid glands, and bleeding. For parathyroid surgery, the main risks are the gland not being cured and, rarely, voice nerve injury. For adrenal surgery, risks include bleeding, injury to nearby organs, and the need for steroid replacement after removal of a cortisol-producing tumor. These risks are lower in the hands of experienced surgeons.
Why the surgeon matters
Surgeon volume independently predicts outcomes after thyroid and parathyroid surgery, and the ATA recommends high-volume thyroid surgeons for operations such as thyroidectomy for goiter. Adrenal guidelines make the same point. Dr. Shifrin is the Director of Endocrine Surgery at CentraState Medical Center, an adjunct clinical assistant professor of surgery at Thomas Jefferson University, board certified in endocrine surgery by the European Board of Surgery and an examiner for the European Board of Endocrine Surgery.
Related pages
References
- Ringel MD, Sosa JA, Baloch Z, et al. 2025 American Thyroid Association Management Guidelines for Adult Patients with Differentiated Thyroid Cancer. Thyroid. 2025;35(8):841-985. doi:10.1177/10507256251363120
- Terris DJ, Snyder S, Carneiro-Pla D, et al. American Thyroid Association statement on outpatient thyroidectomy. Thyroid. 2013;23(10):1193-1202. doi:10.1089/thy.2013.0049
- Inabnet WB, Shifrin A, Ahmed L, Sinha P. Safety of same day discharge in patients undergoing sutureless thyroidectomy: a comparison of local and general anesthesia. Thyroid. 2008;18:57-61.
- Ross DS, Burch HB, Cooper DS, et al. 2016 American Thyroid Association guidelines for diagnosis and management of hyperthyroidism and other causes of thyrotoxicosis. Thyroid. 2016;26(10):1343-1421.
- Bilezikian JP, Khan AA, Silverberg SJ, et al. Evaluation and management of primary hyperparathyroidism: summary statement and guidelines from the Fifth International Workshop. J Bone Miner Res. 2022;37(11):2293-2314.
- Yip L, Duh QY, Wachtel H, et al. American Association of Endocrine Surgeons guidelines for adrenalectomy: executive summary. JAMA Surg. 2022;157(10):870-877. doi:10.1001/jamasurg.2022.3544
- Fassnacht M, Tsagarakis S, Terzolo M, et al. European Society of Endocrinology clinical practice guidelines on the management of adrenal incidentalomas, in collaboration with the European Network for the Study of Adrenal Tumors. Eur J Endocrinol. 2023;189(1):G1-G42.
This page is for general education and does not replace a medical evaluation.




