
 Home
Minimally Invasive Parathyroid Surgery
Minimally invasive parathyroid surgery in Monmouth County, NJ
Dr. Alexander Shifrin is Director of Endocrine Surgery at Atlantic Health CentraState Medical Center in Freehold and performs more than 400 thyroid and parathyroid operations a year. He performs his own parathyroid ultrasound, uses intraoperative PTH monitoring in every operation, and most patients go home the same day, with a small scar and no drain.
Call (732) 792-5003 or request a consultation. Office: 55 Willow Ln, Suite 101, Englishtown, NJ. Patients from Monmouth, Ocean and Middlesex counties and across New Jersey, New York and Pennsylvania are welcome.
Conditions treated Who needs surgery Imaging Your surgery PTH monitoring Recovery Low calcium Scar Complications Postoperative care Pictures FAQ About Dr. Shifrin References
Reviewed by Alexander Shifrin, MD, Director of Endocrine Surgery, CentraState Medical Center. Based on the 2016 American Association of Endocrine Surgeons (AAES) guidelines and the 2022 Fifth International Workshop guidelines on primary hyperparathyroidism.
What is minimally invasive parathyroid surgery?
Minimally invasive parathyroid surgery is the removal of one or several parathyroid adenomas through a small neck incision, placed in the natural skin crease. It includes video-assisted or endoscopic parathyroidectomy, in which the surgeon uses a camera to magnify the view. This speeds up healing and reduces scar formation. Dr. Shifrin uses intraoperative parathyroid hormone (PTH) monitoring to confirm the cure right after the adenoma is removed. About 85% of patients with primary hyperparathyroidism have just one parathyroid adenoma.
Conditions treated:
- Parathyroid adenoma (primary hyperparathyroidism)
- Multiglandular parathyroid disease (parathyroid hyperplasia)
- Secondary and tertiary hyperparathyroidism (kidney-related)
- Reoperative parathyroid surgery
- Familial endocrine syndromes: multiple endocrine neoplasia type 1 (MEN1), MEN2A, MEN4, MEN5, and hyperparathyroidism-jaw tumor syndrome
| Fact | Minimally invasive parathyroid surgery |
|---|---|
| Incision | One small neck incision in a skin crease; about 1.5 cm (less than an inch) to about 3 cm with the open minimally invasive approach |
| Localization | Parathyroid ultrasound plus sestamibi SPECT-CT before surgery |
| Confirmation of cure | Intraoperative PTH monitoring and frozen section |
| Drain | None |
| Skin closure | Skin glue (Dermabond) and dissolvable stitches under the skin |
| Hospital stay | Outpatient; about 3 hours after surgery, and most patients do not stay overnight |
| Return to normal activity | Day-to-day activities within days; no lifting over 20 pounds for 2 weeks |
Who needs parathyroid surgery?
Surgery is the only cure for primary hyperparathyroidism. Medicines can lower calcium or protect bone, but they do not remove the cause. The 2016 AAES guideline says parathyroidectomy is indicated for all patients with symptoms and should be considered for most patients without symptoms, and that it is more cost-effective than observation or medicine. The 2022 Fifth International Workshop recommends surgery to cure the disease, even in patients without symptoms (strong recommendation).
| Reason to operate | Examples |
|---|---|
| Symptoms or complications | Kidney stones, bone loss or fractures, fatigue, bone pain, high calcium symptoms, thirst, constipation, memory or mood changes |
| Test results | Calcium more than 1 mg/dL above the upper normal limit, osteoporosis on a DXA scan, reduced kidney function, high 24-hour urine calcium |
| Age | Under 50 years |
| Other | Patient preference, or when regular monitoring is not possible |
Read more: primary hyperparathyroidism and the hyperparathyroidism FAQ.
Parathyroid imaging before surgery
To perform minimally invasive surgery, preoperative imaging is used to locate the affected gland or glands. The AAES guideline recommends imaging for operative planning, not for diagnosis, and states that patients whose imaging does not show the gland remain surgical candidates. Dr. Shifrin uses two studies:
| Test | What it does | How well it finds the adenoma |
|---|---|---|
| Parathyroid ultrasound (Figure 1) | Dr. Shifrin performs his own ultrasound on every parathyroid patient before surgery, using a high-sensitivity machine at the Parathyroid Center | About 75 to 80% |
| 99mTc-sestamibi SPECT-CT (Figure 2) | Fuses the sestamibi nuclear scan with CT slices using fusion software; dual-phase scan | Identifies the adenoma in about two-thirds of patients |
| Both tests positive and agreeing | Allows a focused, minimally invasive operation | About 90 to 95% |
When these tests do not agree or do not show the gland, other studies such as 4D CT can be used. A negative scan does not rule out surgery.

Figure 1. Parathyroid ultrasound showing right inferior parathyroid adenoma (transverse view)

Figure 2. Sestamibi scan (the same patient as on prior ultrasound, Figure 1)
Your surgery

Minimally invasive parathyroid surgery is performed under high magnification loupes (picture above), and video-assisted surgery is performed with a small laparoscopic camera.
Anesthesia
The procedure is done under general anesthesia. Some patients prefer local/regional anesthesia with general sedation, especially during pregnancy. With the latter, the surgeon can use voice monitoring to avoid injury to the nerves that go to the vocal cords.
Ultrasound and sestamibi SPECT-CT
Small incision, magnification or camera
Blood drawn in the operating room
Pathologist confirms the gland
About 3 hours later
Intraoperative PTH monitoring
Each parathyroid operation is performed with intraoperative parathyroid hormone (PTH) monitoring. Blood tests for PTH are drawn during the surgery. There are at least four measurements:
| Sample | When it is drawn |
|---|---|
| Baseline | Right before surgery begins |
| T-0 | During removal of the parathyroid adenoma |
| T-5 | 5 minutes after the adenoma is removed |
| T-10 | 10 minutes after the adenoma is removed |
The cure is confirmed when the PTH level at 10 minutes (and at 5 minutes) drops by more than 50% from the baseline or T-0 level, whichever is higher. This is called the Miami criterion, developed by Dr. Irvin. The technician assigned to Dr. Shifrin's surgeries performs the PTH measurements in the operating room during each parathyroid procedure.

Roche HITACHI PTH machine. Intraoperative PTH monitoring is performed with the rapid Roche HITACHI PTH machine located in the operating room. Each test takes about 15 minutes.

Parathyroid hormone (PTH) monitoring during parathyroid surgery (tubes)
Intraoperative frozen section (biopsy during the surgery)
Each removed parathyroid gland is sent to a pathologist during the operation to confirm the disease. It is important that a pathologist examine each gland to make sure it is a parathyroid adenoma or hyperplasia. Each gland evaluation takes about 20 minutes.

Parathyroid gland under high magnification microscope
Recovery
Length of hospital stay
Surgery is an outpatient procedure. The average stay after surgery is about 3 hours, and most patients do not need an overnight stay.
Pain
Most patients have little or no pain. Most operations are done under general anesthesia, and pain afterward is minimal. If the operation is done with a local-regional block and light sedation, the neck block lasts about 6 to 8 hours. Some patients feel discomfort or pressure after surgery, which usually goes away within a couple of days. If you have mild pain at home, you can take over-the-counter Tylenol or ibuprofen. An ice pack helps with discomfort or mild swelling: apply it for 10 to 20 minutes every 1 to 2 hours while awake for the first 48 hours. If symptoms do not improve, call our office. Do not drive while taking prescribed pain medicine such as Percocet or another narcotic.
Drain
There is no drain.
| When | What to expect |
|---|---|
| Day of surgery | Go home in about 3 hours. Dissolvable stitches under the skin; skin glue (Dermabond) on the incision. Take your calcium as instructed |
| 2 days after surgery | You may shower. Do not cover the incision; pat it dry; do not scratch or peel the glue |
| 2 to 3 days | Call the office to book your postoperative visit |
| 5 to 7 days | Pathology report usually available |
| About 2 weeks | Skin glue peels off on its own; start scar cream. You may drive and do exercise or heavier activity if your neck moves comfortably |
| 2 to 3 weeks | Postoperative visit: wound check, pathology report, PTH and calcium check |
| 1 to 2 months | Keep the scar out of direct sun |
Scar and stitches
There are no stitches to remove. All stitches are dissolvable and are placed under the skin. The skin itself is closed with a strip of glue, called Dermabond, which stays on the skin for about 2 weeks or until your post-operative visit and then peels off on its own. Do not cover the glue with ointment, band-aids or any other covering. Because the incision is small, closed from underneath and placed in the natural skin crease of the neck, the scar is much smaller than with traditional parathyroid surgery and can be hard to see. Scarring depends on each person's skin healing, and the surgeon makes every effort to achieve the best possible cosmetic result.

Parathyroid adenoma removed during minimally invasive parathyroid surgery

Scar, 2 weeks after the removal of the parathyroid adenoma shown in the above picture (the same patient)
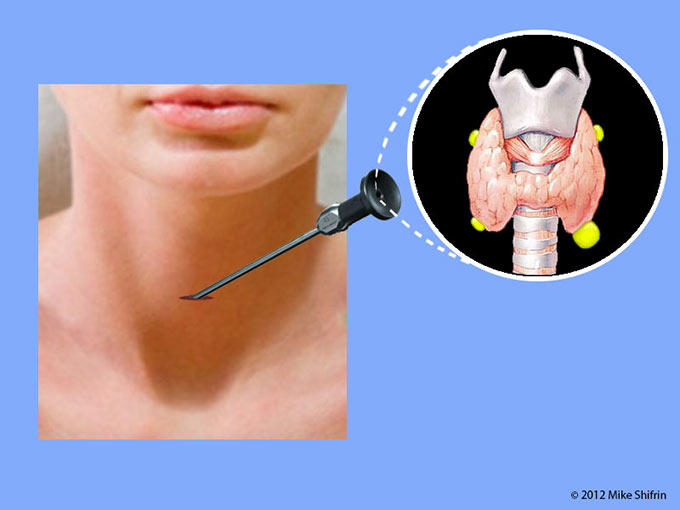
Click on the image to view the video "Minimally Invasive Video-Assisted Parathyroidectomy"
Considering parathyroid surgery?
Dr. Shifrin can review your calcium, PTH and imaging results and explain your options. Call (732) 792-5003 or request a consultation. Office: 55 Willow Ln, Suite 101, Englishtown, NJ. Surgery at Atlantic Health CentraState Medical Center, Freehold, NJ.
Complications
All operations carry some risk, and risk is lower with experienced surgeons. The AAES guideline notes that surgeons who perform a high volume of operations have better outcomes.
| Complication | How often | What it means |
|---|---|---|
| Voice changes (recurrent laryngeal nerve) | 0.5% (1 in 200) lasting nerve injury; about 1 in 50 temporary voice change | Hoarse voice or trouble with high-pitched sounds; temporary changes resolve in 8 to 12 weeks |
| Low calcium | About 1 in 100 patients who had three and a half glands removed for hyperplasia have permanent low calcium | Calcium and vitamin D several times a day for life. All patients go home on a 4-week calcium taper after surgery (see low calcium after surgery) |
| Bleeding | Close to zero with the current technique | Call right away for significant neck swelling or shortness of breath |
| Wound infection | Close to zero with the current technique | No antibiotics are needed unless you have a condition that requires them for every procedure |
If you have signs of low calcium
Low calcium signs: tingling or cramps in both hands and feet, or numbness around the mouth. They usually start a few days after surgery, not in the first 24 hours. Take 2 calcium pills right away and follow the steps in low calcium after surgery.
Postoperative care
- Incision site: the incision is closed with skin glue (Dermabond) that stays on for about 2 weeks or until your post-operative visit. Do not cover it with ointment, band-aids or any other covering. After the glue peels off, you can apply silicone-based scar cream, Mederma or vitamin E lotion 3 to 6 times a day. Avoid sunlight on the wound for 1 to 2 months, especially in summer, because it can cause skin discoloration.
- Physical activity: do not lift anything over 20 pounds. For 2 weeks, avoid activities that cause sweating or straining, and avoid exercise, gardening, lawn care and dusting in an unclean environment. Do not drive while taking pain medicine. Wait about 2 weeks to drive, and until you can move your neck comfortably without restriction. Most patients return to normal day-to-day activities within days. Neck stretching exercise videos are available.
- Shower: you may shower 2 days after surgery. Do not cover the incision; it is fine if it gets wet. Pat it dry with a towel, and do not scratch or peel the glue. Do not soak the incision in a bath or pool, or let water sit on it for a long time.
- Calcium: take calcium carbonate with vitamin D on the 4-week taper from your discharge instructions. See low calcium after surgery.
- Travel: stay in New Jersey for 2 weeks. No air travel and no out-of-state travel.
- Pathology report: usually available within 5 to 7 days.
- Problem calls: call a doctor immediately for significant neck swelling or shortness of breath shortly after surgery, or for low calcium symptoms that do not go away after three doses of calcium.
- Postoperative visit: call the office 2 to 3 days after surgery to book it. You will be seen about 2 to 3 weeks after surgery for a wound check, the pathology report, and PTH and calcium checks.
Open or print the recovery guide (PDF) Print this guide for home, or share it with your family.
Low calcium after surgery
Read this section carefully. Surgery on the parathyroid glands can cause low calcium, because the remaining parathyroid glands, which control your calcium, may stop working for a while. For this reason all patients with a parathyroidectomy or total thyroidectomy go home with instructions to take calcium pills on a 4-week taper. Symptoms of low calcium can start a few days after surgery, usually not in the first 24 hours.
Sample calcium schedule (your exact dose is on your discharge instructions and After Visit Summary):
| Time after surgery | Calcium carbonate 500 mg or 600 mg tablet |
|---|---|
| Week 1 | Every 6 hours |
| Week 2 | Every 8 hours |
| Weeks 3 and 4 | Every 12 hours |
Take the calcium around the clock, without a long break at night. This means waking up once in the night to take it.
Which calcium to buy. You do not need a prescription. Buy it at any pharmacy, health store or online.
- Calcium carbonate 500 mg or 600 mg, with vitamin D (tablets, caplets or capsules).
- Do not substitute calcium citrate.
- Do not buy gummies, Tums, chewables or “once daily” pills.
If you have tingling or cramps in both hands and feet, or numbness around the mouth, your calcium may be low:
- Take 2 calcium pills right away (1000 to 1200 mg, depending on the pill strength).
- Wait 30 minutes. If the symptoms go away, go back to your usual calcium schedule.
- If they do not go away, take 2 more pills and wait another 30 minutes.
- If they still do not go away, take a third dose of 1000 mg. Call the doctor only if the symptoms are still there 30 minutes after the third dose.
Please keep phone calls for emergencies. For questions about the type or timing of your calcium, call during usual office hours at (732) 792-5003.
Constipation can be a side effect of calcium. If it happens, use a stool softener and drink more fluids.
Travel after surgery. For your safety, you must stay in the state for 2 weeks after surgery. No air travel, domestic or international, and no out-of-state travel during this time. If you foresee a travel conflict, speak with Dr. Shifrin before surgery.
Other parathyroid operations
- Multiglandular disease (hyperplasia): when more than one gland is enlarged, the operation removes the abnormal glands, sometimes with part of a gland left in the neck or normal tissue stored (autotransplanted) so calcium stays normal. The AAES guideline says multigland disease should always be considered and that devascularized normal parathyroid tissue should be autotransplanted.
- Secondary and tertiary hyperparathyroidism (kidney-related): surgery is considered when medicines do not control the disease in patients with chronic kidney disease, usually by removing most of the parathyroid tissue.
- Reoperative surgery: an operation after a prior neck operation or a failed parathyroid surgery is more demanding. It relies on careful imaging and is best done by a high-volume parathyroid surgeon.
- Familial syndromes (MEN1, MEN2A, MEN4, MEN5, hyperparathyroidism-jaw tumor): these usually involve several glands, and the operation is planned with genetic counseling. See MEN1, MEN2A and genetic counseling.
Pictures
Scars after parathyroidectomy and parathyroid imaging (see more images)

Scar, 2 weeks after a minimally invasive, VIDEO-ASSISTED (with camera) parathyroid surgery, an approach from the left side.

Scar, 2 weeks after a minimally invasive parathyroid surgery for the large parathyroid adenoma (pictured below).

Scar, 2 weeks after a minimally invasive parathyroid surgery

Scar, 6 months after a minimally invasive surgery for the removal of a parathyroid adenoma

Scar, 3 years after a minimally invasive surgery for the removal of a parathyroid adenoma

Scar, 8 months after minimally invasive parathyroid surgery.

A large parathyroid adenoma 6g, 3.3 cm x 2 cm (removed from the patient pictured above).

Parathyroid adenoma.

A large right upper parathyroid adenoma.

Large parathyroid adenoma.

Parathyroid adenoma.

Video-assisted parathyroidectomy, 1.5 cm (1/3 of an inch) scar 2 weeks after the surgery. The scar after a video-assisted parathyroid surgery is 2 times smaller than with an open minimally invasive surgery (which is about 3 cm, or 1 and 1/5 inches).

A parathyroid adenoma was removed during a minimally invasive parathyroid surgery.

Large parathyroid adenoma, removed during minimally invasive parathyroid surgery.

Scar, 3 weeks after a minimally invasive parathyroid surgery with four parathyroid gland explorations for a non-localized parathyroid adenoma (left lower parathyroid adenoma was found, picture below).

Left lower parathyroid adenoma from the patient pictured above.

Scar, 2 weeks after a minimally invasive parathyroid surgery with removal of the right lower parathyroid adenoma.
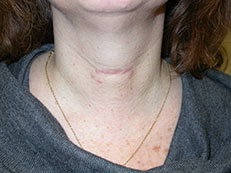
Scar, 2 weeks after parathyroid gland exploration with findings of the right upper 1.5 cm parathyroid adenoma.

Scar, 2 weeks after parathyroid gland exploration with findings of the right lower parathyroid adenoma.

Scar, 4 years after the minimally invasive parathyroidectomy with removal of the right lower parathyroid adenoma.

Scar, 2 weeks after a minimally invasive parathyroidectomy with the removal of the right lower parathyroid adenoma.

Scar, 2 weeks after a minimally invasive parathyroidectomy with the removal of the left upper parathyroid adenoma.

Scar, 10 days after a minimally invasive parathyroidectomy with the removal of the left lower parathyroid adenoma (right after the skin glue came off).
Frequently asked questions
Not always, but surgery is the only cure, and the 2022 international guideline recommends it even for patients without symptoms. Bone loss, kidney stones, reduced kidney function and age under 50 make it more important. You are still a surgical candidate. Imaging helps plan the operation but does not decide whether you need it. An experienced surgeon can explore the neck, and other studies such as 4D CT can be used. Most patients go home about 3 hours after surgery. About 1.5 cm with the video-assisted approach and about 3 cm with the open minimally invasive approach, in a natural skin crease. See the pictures. PTH is measured in the operating room before and after the adenoma is removed, and a pathologist examines the gland during the surgery. No. All stitches are dissolvable and are placed under the skin. The skin is closed with glue (Dermabond) that stays on for about 2 weeks or until your post-operative visit and then peels off by itself. Do not cover it. Yes. All patients go home on a 4-week calcium taper as a precaution: calcium carbonate 500 or 600 mg with vitamin D, about every 6 hours in week 1, every 8 hours in week 2 and every 12 hours in weeks 3 and 4. Your exact dose is on your discharge instructions. Tingling or cramps in both hands and feet, or numbness around the mouth, can mean low calcium. Take 2 calcium pills (1000 to 1200 mg) right away and wait 30 minutes. If it persists, repeat once more and then take a third dose. Call the doctor only if the symptoms are still there 30 minutes after the third dose. Do not drive while taking prescription pain medicine, and wait about 2 weeks to drive and until you can turn your neck comfortably. Do not lift over 20 pounds or do activities that cause sweating or straining for 2 weeks. Stay in New Jersey for 2 weeks, with no air travel. Most patients are back to day-to-day activities within days. Call the office 2 to 3 days after surgery to schedule it. You will be seen about 2 to 3 weeks after surgery for a wound check, the pathology report, and PTH and calcium checks.Do I need surgery if my calcium is only a little high?
What if my scan does not show the parathyroid gland?
Will I stay in the hospital overnight?
How big is the scar?
How do you know the operation worked?
Are there stitches to remove?
Will I need calcium pills?
What should I do if I get tingling or cramps after surgery?
When can I drive, exercise and travel?
When is my follow-up visit?
Related pages
About Dr. Alexander Shifrin

Alexander Shifrin, MD, FACS, FACE, is Director of Endocrine Surgery at Atlantic Health CentraState Medical Center in Freehold, NJ, and Adjunct Clinical Assistant Professor of Surgery at Thomas Jefferson University, Sidney Kimmel Medical College. He completed fellowship training at Penn State Hershey and Columbia/NewYork-Presbyterian, and has authored or edited nine textbooks and atlases on endocrine surgery. He treats thyroid, parathyroid and adrenal disease, and sees patients in Englishtown, NJ.
See also: Primary hyperparathyroidism · Thyroid surgery · Request a consultation


References
- Wilhelm SM, Wang TS, Ruan DT, et al. The American Association of Endocrine Surgeons guidelines for definitive management of primary hyperparathyroidism. JAMA Surg. 2016;151(10):959-968. doi:10.1001/jamasurg.2016.2310
- Bilezikian JP, Khan AA, Silverberg SJ, et al. Evaluation and management of primary hyperparathyroidism: summary statement and guidelines from the Fifth International Workshop. J Bone Miner Res. 2022;37(11):2293-2314. Full text
- Bilezikian JP, Brandi ML, Eastell R, et al. Guidelines for the management of asymptomatic primary hyperparathyroidism: summary statement from the Fourth International Workshop. J Clin Endocrinol Metab. 2014;99(10):3561-3569.
- Irvin GL 3rd, Carneiro DM. Management changes in primary hyperparathyroidism. JAMA. 2000;284(8):934-936.
- Carneiro DM, Solorzano CC, Nader MC, Ramirez M, Irvin GL 3rd. Comparison of intraoperative iPTH assay criteria in guiding parathyroidectomy: which criterion is the most accurate? Surgery. 2003;134(6):973-979.
- Thakker RV, Newey PJ, Walls GV, et al. Clinical practice guidelines for multiple endocrine neoplasia type 1 (MEN1). J Clin Endocrinol Metab. 2012;97(9):2990-3011.
This page is for general education and does not replace a medical evaluation.




