
 Home
Minimally Invasive Parathyroid Surgery
Parathyroid surgery in Monmouth County, NJ
Dr. Alexander Shifrin, Director of Endocrine Surgery at CentraState Medical Center in Freehold, performs minimally invasive parathyroidectomy with a small neck incision, no drain and same-day discharge for most patients.
Call (732) 792-5003 or request a consultation. Office: 55 Willow Ln, Suite 101, Englishtown, NJ.
Jump to: What it is Benefits Who should have it How it is done Videos FAQ Dr. Shifrin's research References
Reviewed by Alexander Shifrin, MD, Director of Endocrine Surgery, CentraState Medical Center. Based on the 2016 American Association of Endocrine Surgeons (AAES) guidelines and the 2022 Fifth International Workshop guidelines on primary hyperparathyroidism.
What is minimally invasive parathyroid surgery?
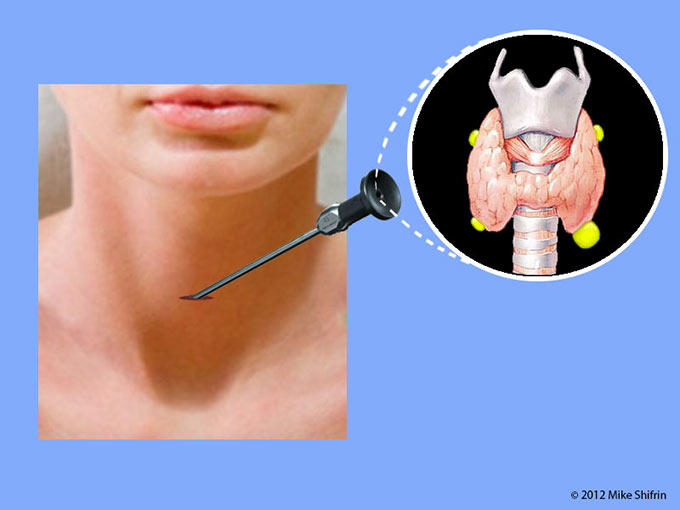
Minimally invasive parathyroid surgery is the removal of one or several parathyroid adenomas through a small neck incision placed in the natural skin crease. Parathyroidectomy is the standard treatment for primary hyperparathyroidism. Two advances made the small operation possible: better imaging to find the abnormal gland before surgery (parathyroid ultrasound and technetium Tc 99m-sestamibi SPECT), and intraoperative parathyroid hormone (PTH) measurement, which confirms during the operation that the disease has been cured. The operation should be done by an experienced parathyroid surgeon after a full preoperative workup that includes blood tests and localizing imaging.
| Fact | Minimally invasive parathyroidectomy |
|---|---|
| Operating time | About 15 minutes to remove a localized adenoma |
| Incision | A small transverse incision in a neck skin crease, usually 2 to 4 cm; the length depends on body build and adenoma size |
| Anesthesia | Usually general anesthesia; a neck block with sedation is an option |
| Drains | None, during or after surgery |
| Closure | Skin glue; on rare occasions, dissolvable stitches under the skin |
| Hospital stay | Same-day surgery; about 3 hours of observation |
| Single adenoma | About 85% of patients with primary hyperparathyroidism |
What does parathyroid surgery do for you?
Surgery cures the high calcium and high PTH. What it can do for your health depends on the problem, and the evidence is stronger for some benefits than others:
| Outcome | What the studies show |
|---|---|
| Calcium and PTH | Cured in most patients when the abnormal gland is removed |
| Bone density | Improves after surgery, usually more than with observation or medicine |
| Fractures | Fewer fractures reported after surgery |
| Kidney stones | Fewer new stones after surgery |
| Symptoms (tiredness, mood, memory, bone pain) | Many patients feel better, but results vary, and these are not a guarantee |
| Heart disease and survival | Some studies suggest benefit, but the evidence is mixed |
The AAES guideline also found that parathyroidectomy is more cost-effective than observation or medicine.
Who should have parathyroid surgery?
Patients with symptoms of primary hyperparathyroidism should have parathyroidectomy. The 2022 Fifth International Workshop recommends surgery to cure the disease even for patients without symptoms (strong recommendation). The list below is for patients without symptoms, and any one item is a reason to refer for surgery:
| Reason | What it means |
|---|---|
| Age under 50 | A longer time ahead for bone and kidney damage |
| High calcium | Serum calcium 1 mg/dL or more above the upper limit of normal |
| Bone loss | Bone density T-score of −2.5 or lower at any site, or a vertebral fracture |
| Kidney problems | Kidney stones, calcium in the kidneys, or reduced kidney function |
For more, see primary hyperparathyroidism and the hyperparathyroidism FAQ.
How is the operation done?
Parathyroid ultrasound and sestamibi scan
Small incision, about 15 minutes for a localized adenoma
PTH measured during the operation
After about 3 hours
- Imaging: the abnormal gland is located before surgery with a neck parathyroid ultrasound and sestamibi scan. This is what makes the small incision possible.
- The incision: a small transverse incision is made in a skin crease, on the side where the imaging found the abnormal gland. Video-assisted (endoscopic) parathyroidectomy uses a camera to magnify the view, which speeds healing and reduces the scar.
- Cure confirmed during surgery: Dr. Shifrin uses intraoperative PTH monitoring to confirm cure right after the adenoma is removed.
- Anesthesia: most patients have general anesthesia. A neck block (regional anesthesia) with sedation, like a colonoscopy, is also an option.
- After surgery: no drain is used. The skin is closed with glue, or on rare occasions with dissolvable stitches, and patients go home the same day after about 3 hours of observation.
Step-by-step details, scar pictures, recovery and complications are on the parathyroid surgery page.

Intra-operative PTH monitoring
High calcium or high PTH?
Dr. Shifrin can review your blood tests, bone density and imaging and tell you whether parathyroid surgery is right for you. Call (732) 792-5003 or request a consultation. Office: 55 Willow Ln, Suite 101, Englishtown, NJ.
Videos
Click on the image to view the video "Minimally Invasive Video-Assisted Parathyroidectomy"
Minimally invasive parathyroid surgery explained (2016)
Frequently asked questions
In the hands of an experienced parathyroid surgeon it is a safe operation, and most patients go home the same day. The American Association of Endocrine Surgeons notes that surgeons who perform many parathyroid operations have better outcomes. For a localized parathyroid adenoma, the operation itself takes about 15 minutes. Preparation, anesthesia, PTH monitoring and waking up add to the total time in the operating room. Surgery is the only cure, and the 2022 international guideline recommends it even in patients without symptoms. It is especially important if you have bone loss, kidney stones, reduced kidney function, calcium well above normal, or are under 50. You are still a surgical candidate. Imaging helps plan a smaller operation, but it does not decide whether you need surgery. Studies have shown that negative imaging uses more hospital resources, which is why an experienced surgeon matters. No drain is placed. The skin is closed with skin glue, or rarely with dissolvable stitches under the skin. Most patients go home after about 3 hours of observation. Most patients have general anesthesia. A neck block with sedation (like for a colonoscopy) is an option for some patients.Is parathyroid surgery safe?
How long does the operation take?
Do I need surgery if I have no symptoms?
What if my scans are negative?
Will I have a drain or stitches to remove?
How long do I stay in the hospital?
Which anesthesia is used?
Dr. Shifrin's research on parathyroid surgery
- Harari A, Allendorf J, Shifrin A, DiGiorgi M, Inabnet W. Negative preoperative localization leads to greater resource utilization in the era of minimally invasive parathyroidectomy. Am J Surg. 2009;197(6):769-773. (PDF)
- Shifrin A, LiVolsi V, Zheng M, et al. Neuroendocrine thymic carcinoma metastatic to the parathyroid gland that was reimplanted into the forearm in a patient with multiple endocrine neoplasia type 1 syndrome: a challenging management dilemma. Endocr Pract. 2013. (PDF)
Related pages
References
- Bilezikian JP, Khan AA, Silverberg SJ, et al. Evaluation and management of primary hyperparathyroidism: summary statement and guidelines from the Fifth International Workshop. J Bone Miner Res. 2022;37(11):2293-2314. Full text
- Wilhelm SM, Wang TS, Ruan DT, et al. The American Association of Endocrine Surgeons guidelines for definitive management of primary hyperparathyroidism. JAMA Surg. 2016;151(10):959-968. doi:10.1001/jamasurg.2016.2310
- Bilezikian JP, Brandi ML, Eastell R, et al. Guidelines for the management of asymptomatic primary hyperparathyroidism: summary statement from the Fourth International Workshop. J Clin Endocrinol Metab. 2014;99(10):3561-3569.
- Augustine M, Bravo P, Zeiger M. Surgical treatment of primary hyperparathyroidism. Endocr Pract. 2011;17(Suppl 1):75-82.
- Harari A, Allendorf J, Shifrin A, DiGiorgi M, Inabnet W. Negative preoperative localization leads to greater resource utilization in the era of minimally invasive parathyroidectomy. Am J Surg. 2009;197(6):769-773.
This page is for general education and does not replace a medical evaluation.




